
| Finding | What is established | Planning use |
|---|---|---|
| Defining lesion | Perivascular accumulation of neuronal phosphorylated tau at the depths of cortical sulci, variably with astrocytic aggregates | Look for this pattern in sections, not for tau alone, when deciding whether a case meets criteria. |
| Timing of diagnosis | Definitive diagnosis only by postmortem neuropathological examination | Treat a diagnosis in a living person as a clinical syndrome, not a confirmed pathology. |
| Exposure history | Over 97% of published cases had known repetitive head impact exposure | Use exposure history to justify a thorough brain examination, not to forecast the result. |
| Individual prediction | Head-injury history trend too weak to predict CTE-NC in an individual | Do not infer pathology from history alone. |
| Tau biochemistry | Distinct p-tau fibril structure, unlike ageing, Alzheimer disease and other tauopathies | Keep CTE separate from other tau pathologies when reporting. |
These points come from the consensus criteria for CTE neuropathological diagnosis and a routine autopsy series applying them.
Chronic traumatic encephalopathy pathology is defined by a perivascular accumulation of phosphorylated tau at the depths of cortical sulci. A definitive diagnosis can be made only at postmortem examination.
CTE is one of the types of neurodegenerative diseases recognised by a protein pattern in tissue. This guide explains what that pattern is, how the criteria and stages use it, and what remains unsettled outside the autopsy room.
Practical consequences of an autopsy-only diagnosis
The most important consequence is that CTE cannot be confirmed in a living person. The consensus criteria state that CTE can be definitively diagnosed only by postmortem neuropathological examination. The corresponding clinical condition is called traumatic encephalopathy syndrome (TES), which describes a clinical picture rather than a proven pathology.
That separation shapes how findings should be read and communicated:
- Clinical labels: Use TES for a living person with a suggestive syndrome. Reserve the term CTE for cases with the pathology confirmed in tissue.
- Requesting an examination: A history of repetitive head impacts is a reasonable reason to ask for a full neuropathological assessment with tau immunostaining. It is not a substitute for one.
- Interpreting history: In a routine autopsy series, the link between head-injury history and CTE neuropathologic change was too weak to predict the presence of CTE-NC in an individual. A negative history does not exclude the pathology, and a positive one does not establish it.
- Reporting wording: Describe the pathology in the lesion terms the criteria use, and avoid implying that the pathology explains a particular person’s symptoms.
These limits matter because the pathological definition is precise while the clinical picture is not. The next sections show how precise the tissue definition is.
What the NINDS consensus criteria established
The NINDS-NIBIB criteria for the neuropathological diagnosis of CTE were published in 2016 and refined in 2021. They gave pathologists a shared definition of the lesion, so cases from different brain banks could be compared. The 2023 update was published in Acta Neuropathologica in April 2023, as listed by the Boston University CTE Center.
Since the criteria appeared, hundreds of contact sport athletes and others have been diagnosed with CTE at postmortem examination, according to the consensus paper. The criteria turn a visual pattern into a yes-or-no call. The 2021 consensus describes the CTE-associated p-tau lesion as distributed around small blood vessels at the depths of cortical sulci in an irregular pattern. A pathologist who sees tau scattered diffusely through the cortex has not found this lesion. One who sees tau clustered around vessels in sulcal depths, in a patchy distribution, has.
Perivascular tau at sulcal depths: the defining lesion
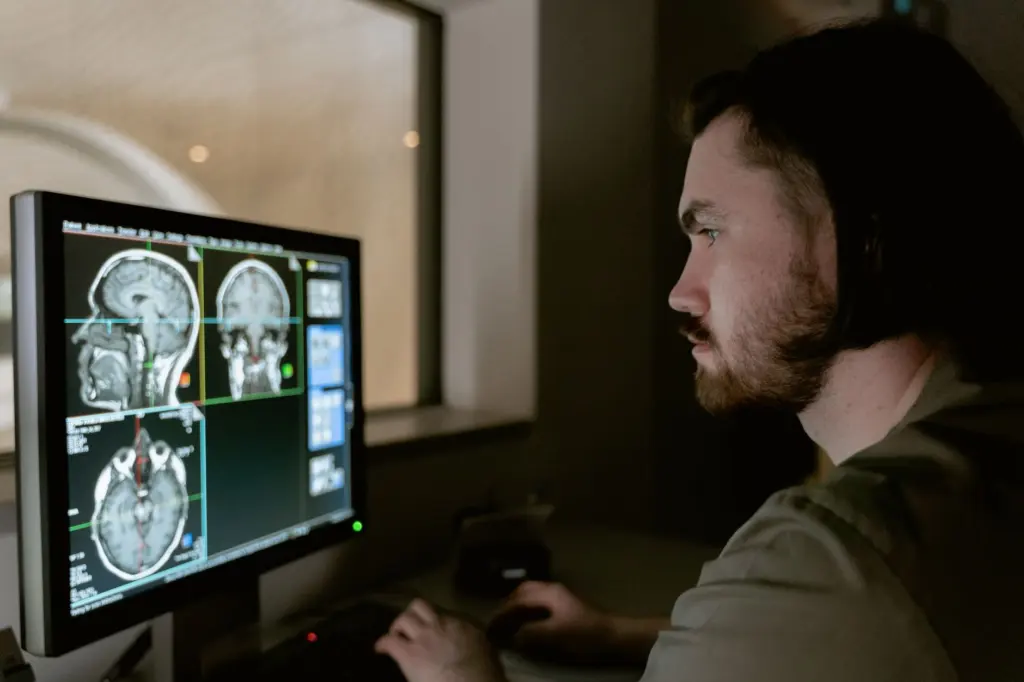
The pathognomonic lesion of CTE is a perivascular accumulation of neuronal phosphorylated tau at the depths of cortical sulci, variably accompanied by astrocytic aggregates. Perivascular tangles are the element that makes the lesion recognisable. Tau-positive neurons collect around a small vessel, and the vessel sits in the depth of a sulcus.

The location is not arbitrary. Computational models predict the perivascular and sulcal location of p-tau after head impact, which links the lesion’s geography to the mechanics of repetitive head impact. This supports the pattern as a physical consequence of impacts, though the models predict where tau accumulates and do not by themselves establish how impacts cause disease.
For practical review, check three things in a section: whether tau is in neurons, whether it surrounds small vessels, and whether it concentrates at sulcal depths. All three together define the lesion.
How CTE tau differs from Alzheimer and ageing tau
CTE tau differs from Alzheimer and ageing tau in two ways. First, the p-tau fibrils in CTE have a distinctive molecular structural configuration, unlike the changes seen with ageing, Alzheimer disease and other tauopathies. Second, the lesion’s distribution is different, being perivascular and sulcal rather than following the patterns of those conditions.

This matters because tau is common in older brains, and the criteria must keep CTE from being confused with unrelated tau changes. In the 2021 consensus work, CTE-NC p-tau deposits were distinguished from age-related tau astrogliopathy (ARTAG), early tau-only lesions and primary age-related tauopathy. For a fuller picture of the latter, see primary age-related tauopathy. For a disease with an entirely different pathological signature, compare huntington’s disease pathology.
Tau isoform ratios are often used to characterise tauopathies, but the fibril structure is the distinguishing feature the criteria rely on. In routine diagnosis, the spatial pattern on immunostaining does the work.
CTE stages I to IV and severity grading
CTE is staged from I to IV in the McKee scheme, which describes how far the tau pathology has spread. Early stages involve restricted cortical foci. Later stages involve wider cortical and deeper involvement, which is why the staging image below compares cortex and hippocampus across the four stages. The detailed regional criteria for each stage are set out in the McKee staging publications and the consensus paper, and should be consulted directly when a stage must be assigned.
The 2021 refinements added a simpler way to express severity. A routine autopsy series reported in the Journal of Neuropathology and Experimental Neurology graded cases as low or high CTE-NC. Of the cases with CTE-NC, 9 of 16 were low and 7 of 16 were high. All brains were sampled widely, with 12 to 18 regions per brain, because a lesion that is patchy and sulcal can be missed by narrow sampling.
Sampling breadth is therefore a practical safeguard. A stage or grade is only as reliable as the number of regions examined and stained for tau.
Exposure and risk
Repetitive head impact is the exposure most closely tied to CTE. Over 97% of published CTE cases have been reported in individuals with known exposure to repetitive head impacts, and the consensus paper describes a robust dose-response relationship between CTE and years of American football play. The main proposed risk factor is repeated mild head injury, and APOE e4 may add risk.
These findings come from autopsy series, which are drawn from people whose brains were donated or examined, so they show association within that group. They do not give the chance that any individual with a given exposure will develop CTE, and the autopsy-series finding on history, noted earlier, shows why.
Frequently asked questions
What is traumatic encephalopathy syndrome?
It is the clinical condition that corresponds to CTE. It is recognised in life by symptoms, whereas CTE itself is a pathological diagnosis made in tissue.
Is CTE found only in American football players?
No. Hundreds of contact sport athletes and others have been diagnosed postmortem. The dose-response finding is specifically with years of American football play.
How common was CTE-NC in a routine autopsy series?
In the series reported in 2023, 85 adult cases were immunostained for p-tau and 69 were negative for CTE-NC.
Do the criteria depend on tau alone?
No. Tau must be phosphorylated, neuronal, perivascular and at sulcal depths, with the pattern distinguished from ageing-related and other tau lesions.

Leave a Reply